The diseaseEntry 01.2
Carcinoma in situ
What was established
The classification that depends on a wall: when cells have changed but not yet left

The boundary that changes everything
Breast tissue is a branching system of ducts and lobules, each enclosed by a basement membrane — a thin but structurally decisive layer of collagen and glycoprotein. When epithelial cells within those structures acquire malignant characteristics, the question of whether those cells have crossed the basement membrane determines almost everything that follows: how the disease is classified, how it behaves, and how it has historically been treated. Cells that remain entirely on the inside of that wall are classified as carcinoma in situ, Latin for "carcinoma in place." Cells that have breached it enter the category of invasive carcinoma, and the clinical calculus changes immediately.
Two distinct forms of carcinoma in situ are recognised. Ductal carcinoma in situ, known by the initialism DCIS, arises in the ducts themselves. Lobular carcinoma in situ, or LCIS, arises in the lobules — the terminal milk-producing units. They differ not only in location but in what they are now understood to represent clinically. DCIS has long been treated as a direct precursor to invasive disease. LCIS is more accurately described as a marker of elevated risk across both breasts rather than a lesion obliged to progress. That distinction has had significant consequences for how each is managed, and the two conditions are no longer grouped as interchangeable entities in any major classification system.
Lifted out of the flow
Key distinction
- Carcinoma in situ vs invasive carcinomathe basement membrane is the structural boundary; crossing it changes the classification entirely
- DCIS (ductal)treated as a potential precursor to invasive disease; found mainly by mammography as microcalcifications
- LCIS (lobular)now understood as a bilateral risk marker rather than a direct precursor; mostly incidental finding on biopsy
How the diagnosis was made possible
Carcinoma in situ was recognised pathologically long before it could be detected in living patients at any useful scale. The cellular abnormalities that define it — nuclear enlargement, loss of polarity, mitotic activity — are visible under a microscope once tissue has been excised and stained, but the lesion produces no palpable mass, no symptom detectable by the person carrying it, and no reliable clinical sign in most cases. Before the widespread availability of mammography, DCIS was therefore a rarity in clinical practice, encountered mainly as an incidental finding in tissue removed for another reason. It was not rare in the tissue itself; it was invisible until the technology to find it arrived.
Robert Egan standardised mammographic technique in Houston in the late 1950s, and the subsequent spread of the method into population screening changed the epidemiology of DCIS almost entirely. The lesion is now detected most often as microcalcifications on a mammogram — calcium deposits that form within necrotic material inside ducts — rather than as a palpable lump. This shift in how the diagnosis arises has been at the centre of the screening debate ever since: a diagnosis driven by imaging rather than by symptoms produces a different population of cases, not all of which would have progressed to cause harm. LCIS, which does not calcify reliably, remains largely an incidental finding on biopsy taken for other lesions.
Classification within carcinoma in situ
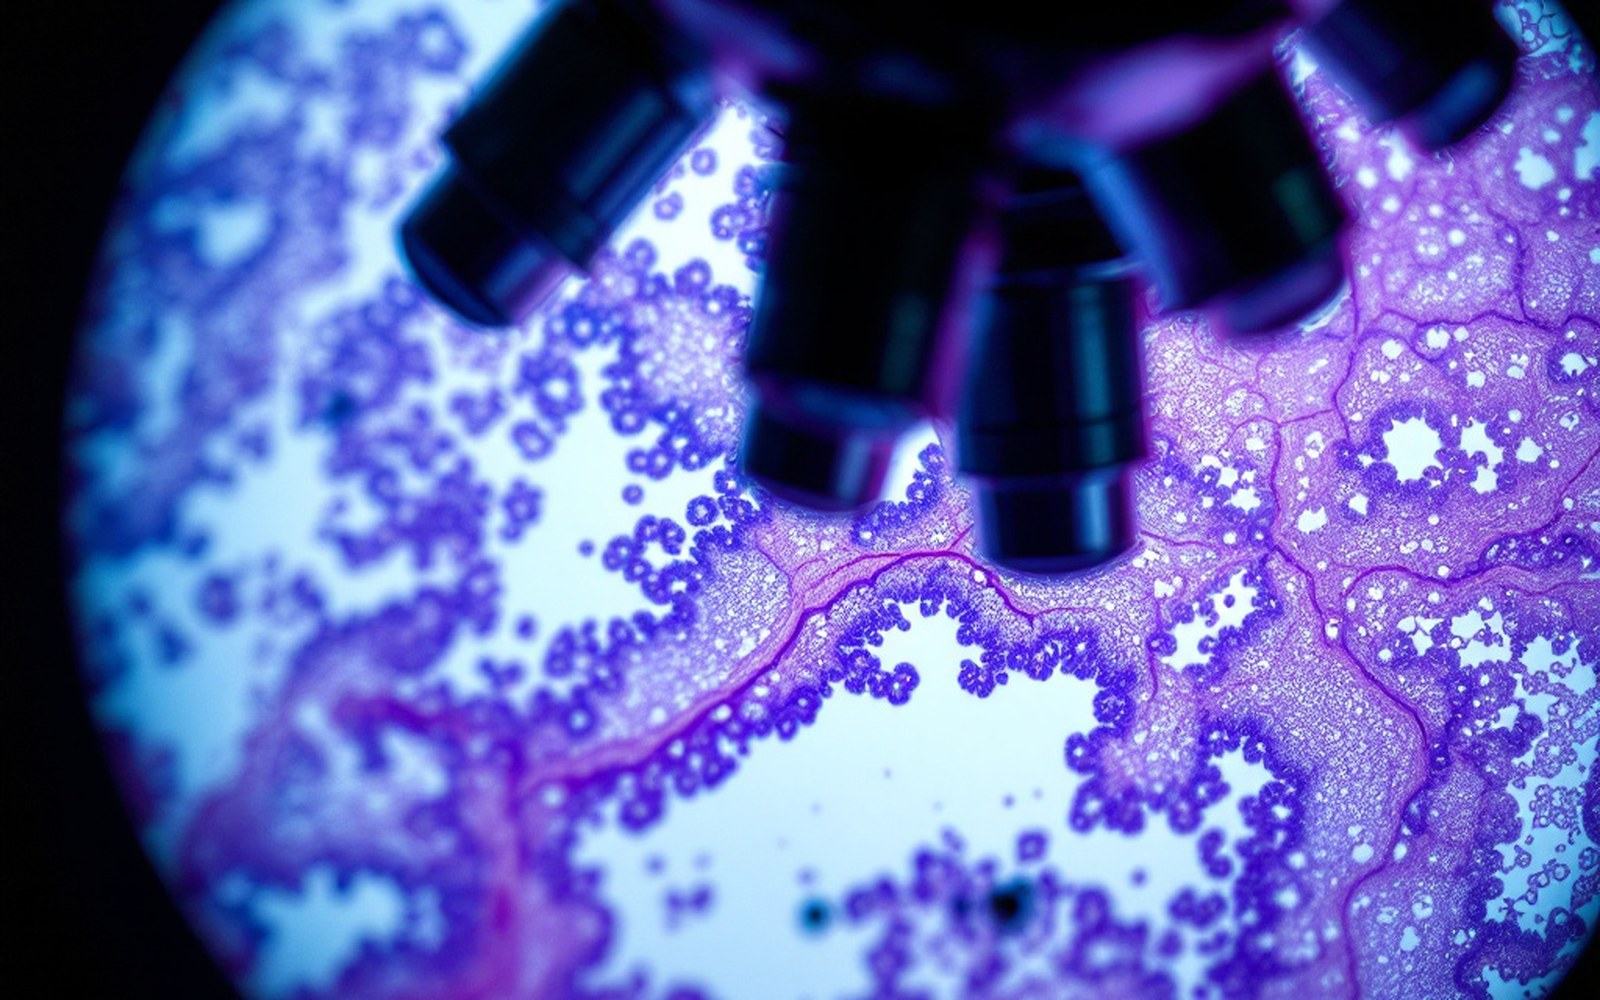
DCIS is itself a heterogeneous category. Pathologists classify it by architecture — solid, cribriform, micropapillary, papillary — and by nuclear grade, a measure of how abnormal the cells look. The grade matters because it correlates, imperfectly but meaningfully, with the probability of local recurrence and with the likelihood that invasive disease will be found nearby. High-grade DCIS, often associated with central necrosis and the "comedonecrosis" pattern visible on histology, behaves differently from low-grade lesions characterised by uniform, small, well-organised cells. The oestrogen receptor is expressed in a majority of DCIS cases, particularly lower-grade ones, which has implications for hormonal strategies aimed at reducing the risk of subsequent invasive disease.
The Van Nuys Prognostic Index, first described in the 1990s, attempted to formalise the prediction of local recurrence in DCIS by combining nuclear grade, necrosis, tumour size, and margin width. It influenced surgical planning at many institutions, though its prospective validation has remained contested. No scoring system has displaced the fundamental dependence on complete pathological assessment of excised tissue.
Pathologists classify it by architecture — solid, cribriform, micropapillary, papillary — and by nuclear grade, a measure of how abnormal the cells look.
LCIS, meanwhile, was reclassified conceptually across several decades. Originally described by Joseph Albores-Saavedra and colleagues working from earlier observations, it was for many years treated with mastectomy on the reasoning that it was a direct precursor. The evidence from long follow-up studies shifted the consensus: women with LCIS who were monitored rather than operated upon developed invasive carcinoma at rates roughly eight to ten times the background population risk, but the invasive cancers arose in either breast with roughly equal frequency — behaviour inconsistent with a lesion progressing directly and locally. A variant called pleomorphic LCIS, recognised more recently, may carry a higher intrinsic risk and is treated with greater caution, though the evidence base for it is thinner.
The overdiagnosis problem, stated precisely
The epidemiological shift produced by screening — from a rare incidental finding to a major component of detected breast pathology — brought DCIS into the centre of the screening argument with particular force. The World Health Organization's International Agency for Research on Cancer assessed screening evidence and acknowledged that while DCIS detection increases substantially with mammographic screening, the proportion of DCIS cases that would have progressed to clinically significant invasive disease if left undetected is genuinely unknown. That uncertainty is the core of what is meant by overdiagnosis in this context: not a misdiagnosis, but the detection and treatment of a lesion whose natural history would never have harmed the patient. The histology is real; what is uncertain is the trajectory.
This uncertainty has driven a body of research aimed at identifying which DCIS cases can safely be managed conservatively. Randomised trials — including the COMET trial in the United States and the LORD trial in Europe — are currently comparing active surveillance against standard surgical treatment for low-grade DCIS specifically. Their results are awaited. In the meantime, surgical excision, with or without radiotherapy and with or without hormonal treatment depending on receptor status, remains standard practice, resting on the principle that the tools to reliably distinguish the lesion that will progress from the one that will not are not yet in routine clinical use.
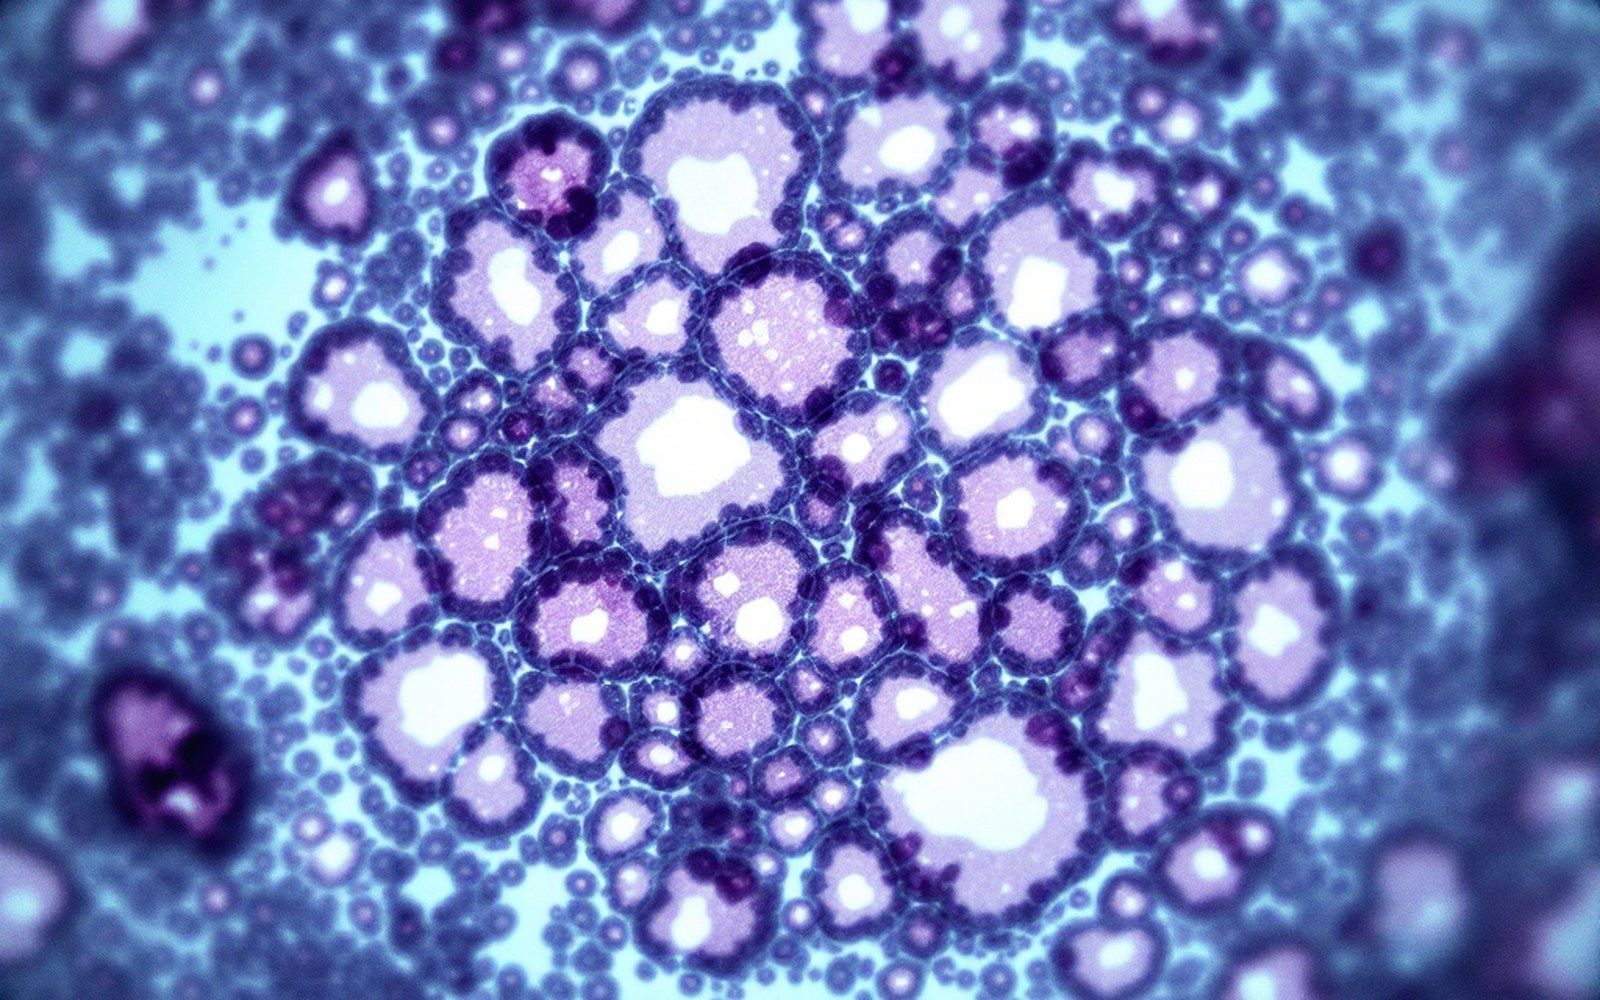
The line drawn by a basement membrane is, for the time being, the best boundary medicine has.
Lifted out of the flow
The numbers problem
- DCIS was rare in clinical practice before mammography; now a large proportion of screen-detected breast pathology
- LCIS follow-up studies: invasive cancers at roughly 8–10× background risk, spread across both breasts equally
- COMET and LORD trials ongoingresults pending at time of writing
Elsewhere in the disease
- Ducts and lobulesThe tissue is a branching system of ducts ending in lobules, and almost everything that follows depends on which part a growth started in.
- Invasive carcinomaOnce the basement membrane is breached the classification changes and so does everything downstream of it.
- Grade and stageGrade describes how the cells look and stage describes how far they have gone; the two are routinely confused and mean different things.